

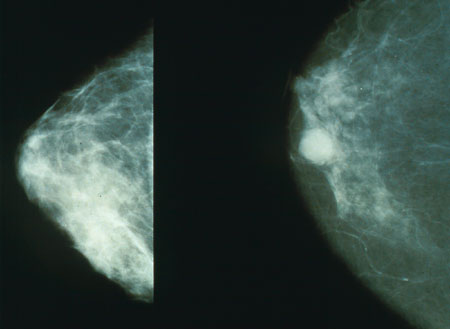
The New York Times, one of whose hobbyhorses is overtesting for and overtreatment of women’s breast issues, has decorated the front page with the latest report on DCIS (ductal carcinoma in situ, a poorly named condition that may or may not be a breast cancer precursor). Some 60,000 women a year are diagnosed with this vaguely understood malady (if malady it is), and most are treated with lumpectomy plus unpleasant chemicals plus unpleasant radiation or with mastectomy, with or without the added unpleasantries. Many of us, myself among them, opt for double mastectomy, just to end the torture.
And the Times reports that all the frenetic treatment does just about nothing to change the outcome: that women with DCIS are no more likely to die of breast cancer than the ordinary woman on the street, a member of the “general population.” Those who do die — an extremely small percentage — “die despite treatment, not for lack of it.”
Yes. Well, this is not exactly news. The study, published yesterday in JAMA Oncology, essentially confirms what we already know: the widespread hysteria over breast cancer and the frantic push to screen every woman on the planet with mammography lead to widespread unnecessary treatment and mutiliation, accomplishing rather little.
I knew this at the time I got sucked into the mammography/mastectomy vortex. One of my doctors, an oncologist, openly admitted I was probably being subjected to unnecessary treatment. But the problem was then — as it still is now — that so little is known about DCIS that doctors and patients alike are afraid to take risks with it.
Possibly as many as 80% of DCIS occurrences may never evolve into invasive cancers. Estimates range from as few as 20% of cases to as many as 50% of cases turn into cancer. We do not know the correct figures, but we do know that some proportion of DCIS does morph into invasive malignancy.
Why do we not know? Obviously, since we have established that the phenomenon can signal the advent of or turn into invasive cancer, it would be monstrously unethical and immoral to leave, say, 10,000 women untreated while treating another group of 10,000 women with the tools we presently have, just to compare the outcomes. So…we cannot subject this ailment (if it is an ailment) to the gold standard of scientific research.
We can make some inferences, though, based on observation.
What we’ve seen over the decades since we began treating DCIS as though it were cancer is that for women over 40 who are not Black, the outcomes have not changed. Dr. Laura Esserman, probably the leading exponent in the movement calling for some sanity around this issue, points out that if life-threatening invasive breast cancers start out as DCIS, then deaths from such cancers should have dropped dramatically as detection rates have skyrocketed. But that’s not what’s happened at all:
During the 1980s, before the mammography enthusiasm, women found to have DCIS numbered in the hundreds. Today, 60,000 women are treated for it every year. And there has been no change in the rates of true cancers.
Some researchers in the minimalist camp feel that most women should not be treated for DCIS, other than perhaps to remove the aberrant cells. Eighty percent of women with DCIS are not in the high-risk categories — young or black women or those with tumors bearing telltale genetic markers; that 80 percent may be fine with no treatment.
How do I feel about this, after a year of disruptive, painful, and frightening treatment culminating in removal of both breasts?
Well, of course it pisses me off. But not much.
In the first place, there was an outside chance that the DCIS in my right breast, which was extensive and probably had been there for many, many years, might have morphed into a cancer that could have killed me before some other natural cause picked me off. As a practical matter, it’s far more likely that I’ll die of cardiac disease. It’s probably more likely that I’ll die in a car wreck. But why invite trouble?
The surgery accomplished two things:
1. Lowered my chance of developing a breast cancer to something less than 1 percent; and
2. Obviated the need for tamoxifen or aromatase inhibitors (both of which have some very nasty side-effects) and for radiation therapy (whose very nasty side-effects can surface 30 years after the fact).
It also brought a stop to the unpleasant and bothersome trips to the mammography machine. I will never have to get another mammogram again, thank God, because there’s nothing left to mammographize. 😀
If I had been much younger, say in my 40s or even 50s, yes, I’d have been very upset about being converted into a boobless wonder. However, at my age…well, I see it as cosmetic surgery! It removed two unsightly blobs of flesh that were competing to see which one could reach my bellybutton first.
And what a boon, to be able to walk out the front door without first having to get oneself lashed up in straps and cantilevers! The comfort level and the simplicity factors are amazing.
There are, however, some assumptions the supposed experts make about mastectomy veterans that annoy the hell out of me.
For example, we are repeatedly told that women who ask for a double mastectomy do so because they’re terrified that the condition will “come back” in the other breast. We are assumed to be so stupid that we don’t understand that a cancer (or a DCIS, apparently) in breast A does not “come back” in Breast B; we can’t get it through our silly little heads that a recurrence in the contralateral breast is a new entity, not a spread from the original site.
And we’re thought to be unable to grasp what our real risk of recurrence is — i.e., very low. Whenever the subject of elective double mastectomy pops up in the media, invariably the language states that women do this “to be safe” or “as a precaution.”
No. Women do this because they don’t want to be lopsided.
Some women are bright enough to figure out exactly how harrowing breast “reconstruction” is — and how unlikely it is to lead to a truly satisfactory outcome. Quite a few women who opt for double mastectomy after some condition has appeared in only one boob do so because they’re choosing to go flat: because they choose not to put themselves through months (in some women’s cases, through years) of painful surgery.
If you decide you are not going to have a bag of silicone gel implanted under your pectoral muscles or you are not going to allow a doctor to slice flesh off some other part of your body and slap it on your chest, then it makes sense to have both boobs removed, so that you will not be uneven. This obviates back and neck pain, posture issues, and problems with clothing.
With a tabula rasa for a chest, I can go out without any artificial accouterments — almost all of my existing clothing accommodates this — or if I please, I can use one of my old bras (not one of those radically expensive special mastectomy bras) and fill it with knitted foobs that are very comfortable and, shall we say, amazingly convincing. Instant va-va-voom, if I so please… 😉
Another aspect of the breast cancer mania that I find extremely annoying is the screening enthusiasts’ hoots about five- and ten-year “survival” rates.
In the first place, most breast cancers are pretty slow-growing. From start to finish, such a malignancy is likely to take more than five years to kill its victim.
Second, the advent of hypersensitive screening mammography skews the reality of supposed survival rates by detecting conditions at an early stage without changing the fact that the condition is going to kill you by a given date anyway. Here’s how it works.
Let us suppose you develop a malignancy that will spirit you away in eight years, no matter what. It has few symptoms, and so you are unlikely to notice it until fairly late in the game, say, two or three years before you die.
If your cancer is detected, two, three, or four years before it would naturally do you in, then you are said not to have survived for five years with it.
But let’s suppose the very same malignancy is spotted by an ultra-sensitive mammogram, only it’s spotted after it’s been there for, say, two years. You have surgery, radiation, and chemotherapy, but in fact the thing has spread around and you’re a goner. You’ll be a goner after it’s been in your body for eight years — no matter when it is discovered. Because it was discovered six years before you die with it, you appear to have survived for longer than five years. Thus, presto-changeo, you are counted and touted as among the “five-year survivors.” Even though you have survived nothing.
You host the disease for the same amount of time. Your survival of the disease has not changed. Nothing has changed except the deployment of a piece of equipment that for many women makes little difference in the number of years remaining.
Along the same line, women who are operated on, drugged, and irradiated for DCIS are dubbed “survivors.” That is ridiculous. The mortality rate for DCIS is extremely low. Many, possibly most, of them would have lived a normal life span whether or not their DCIS was discovered, and whether or not it was treated. DCIS is not cancer!
“Survivors.” {snort!} I find that term excruciatingly annoying. I am not a survivor. A patient, yes. Probably a victim, yes. But “survivor”? Give me a break!
When you are sick, you are not at war. You are just sick. You are not doing battle. You are suffering a disease and hoping you will get over it or will not suffer unduly at your dying. You are not fighting. You are undergoing treatments that other people apply to you. You are not a hero, you are not a warrior, you are not a survivor. You’re a sick person.
Then we have the cutesy term “lumpectomy.” Doesn’t it sound better than “mastectomy”? No one wants to tell the little woman, of course, that a lumpectomy is a form of mastectomy: it’s a partial mastectomy, also called a “quadrantectomy” or a “segmental mastectomy.”
Nor does anyone bother to clue you that the re-excision rates for lumpectomies — repeat surgeries to go back in after “missed” cells — are simply phenomenal. On average, re-excision rates stand at over 30 percent. However, they vary by doctor, with some surgeons racking up re-excisions rates of 70 percent.
God, I hate sugar-coating. It’s impossible for me to imagine that most adults would prefer to have treatment delivered to them swaddled in euphemism.
Do we really need to be subjected to childish prattle to be able to deal, as grown-ups, with the inevitable? Why?

